
Medical Terminology Daily (MTD) is a blog sponsored by Clinical Anatomy Associates, Inc. as a service to the medical community. We post anatomical, medical or surgical terms, their meaning and usage, as well as biographical notes on anatomists, surgeons, and researchers through the ages. Be warned that some of the images used depict human anatomical specimens.
You are welcome to submit questions and suggestions using our "Contact Us" form. The information on this blog follows the terms on our "Privacy and Security Statement" and cannot be construed as medical guidance or instructions for treatment.
We have 701 guests online

William S. Halsted, MD
(1852 – 1922)
American anatomist, teacher, and surgeon, William Stewart Halsted was born in New York City, USA to a wealthy family of English origin. His father was involved in charitable work and Governor and trustee to a city hospital. Not a brilliant student initially, Halsted took an undergraduate in Liberal Arts in Yale, CT., after which he entered the Medical College of Physicians at the Columbia College, where he excelled.
As a second-year medical student Halsted applied and obtained a position in surgery at a local hospital. In here he learned about Lister’s antiseptic technique and became an adamant proponent of it to reduce infection. In 1877 Halsted obtained his MD. After a short time as House Physician at the New York Hospital, Halsted traveled to Europe to further his education studying for two years at the Universities of Vienna, Leipzig, and W?rzburg.
Besides being at the forefront of surgical and antiseptic techniques (introducing the use of rubber gloves in surgery), Halsted was extremely concerned with the way medical students were taught in the US. He pioneered bedside clinical round discussions with the medical students after two years of basic sciences studies. Halsted developed the idea of a patient chart; he also developed the residency program for medical students in use today.
Halsted is probably the most influential researcher and surgeon at the turn of the century. He dedicated time to the study of intestinal anastomoses and the use of silk as a suture material. His experimental work in 1887 proved that the inclusion of the submucosa layer in an anastomosis was mandatory, as well that a single layered anastomosis was enough to attain closure. Perhaps Halsted’s most important contribution was the application and use of the scientific method to surgical questions. Halsted’s principles, also known as "Halsted's Rules of Surgery", set the standards used today in surgical suturing and surgical stapling.
He also pioneered the development and surgical techniques for radical mastectomy as a treatment for breast cancer.
As a side effect of this studied in anesthesia and the use of cocaine for anesthesia, Halsted became addicted to this substance, a problem that followed him through the years. Without impairing his capacity as a researcher and a surgeon, Halsted eventually recovered. He died in Baltimore in 1922 as a complication to surgery.
Sources:
1. Dubay, A. D., & Franz, G. M. (2003). Acute Wound Healing: The Biology of Acute Wound Failure. Surg Clin NA, 83, 463-481.
2. Halsted, W. S. (1887). Circular Suture of the Intestine - An Experimental Study. Am J Med Sci, 436-461.
3. “William Stewart Halsted: his life and contributions to surgery” Osborne, P. Lancet Oncol 2007; 8: 256–65
4. “William Stewart Halsted: Surgical pioneer” Burress, P Endoc Today (2010), 8: (2) 22
5. “William Stewart Halsted (1852–1922) Neurological stamp” Haas, LF J Neurol Neurosurg Psych 2000;69:641
Original image courtesy of "Images from the History of Medicine" at www.nih.gov
"Clinical Anatomy Associates, Inc., and the contributors of "Medical Terminology Daily" wish to thank all individuals who donate their bodies and tissues for the advancement of education and research”.
Click here for more information


- Details
- Written by: Efrain A. Miranda, Ph.D.

Dr. José Manuel Revuelta
Personal Note: This is article originally published in Spanish by Dr. Jose Manuel Revuelta, a a Professor of Surgery and Professor Emeritus at the University of Cantabria. Former Head of Cardiovascular Surgery at Valdecilla Hospital in Santander, Spain. Dr. Revuelta has contributed several articles to this blog
The article's title (in Spanish) is "La Libertad del Corazón" (The Freedom of the Heart), a discussion of the heart's independence from the nervous system.
He has graciously granted us permission to translate and publish his article in “Medical Terminology Daily”. Dr. Miranda.
The Freedom of the Heart
There is a common belief that if the brain stops functioning, the body collapses instantly and the heart stops. The heart is not merely an executor of the brain's commands, but a central organ with astonishing self-governance. In fact, if we were to isolate a human heart in a suitable, oxygenated, and nutrient-rich environment, it would continue to beat autonomously, as we observe every day in donor organs for transplantation.
This capacity for self-excitation resides in its automaticity, a property of a group of specialized cells (the sinoatrial or sinus node) that acts as a biological pacemaker. Located in the upper wall of the right atrium, this peculiar cluster of cells spontaneously generates its own electrical activity rhythmically, triggering heart contractions without needing any impulse from the cerebral cortex or brainstem.
After reading this, we wonder about the true role of the brain in directing and coordinating the human body. More than a conductor creating the music, the brain acts like a sound engineer adjusting the volume and rhythm according to the needs of the environment. Through the nervous system, the brain operates pedals to accelerate (sympathetic nervous system, driven by norepinephrine) or decelerate the heart (parasympathetic nervous system, guided by the vagus nerve and acetylcholine).
When we run or feel fear, the brain commands the heart rate to accelerate; when we sleep, it presses the brakes, so the heart functions more calmly. In a healthy person, the moment-to-moment interaction between the sympathetic and parasympathetic nervous systems generates micro-oscillations in the interval between heartbeats (R-R interval), a variability that reflects the system's adaptability.
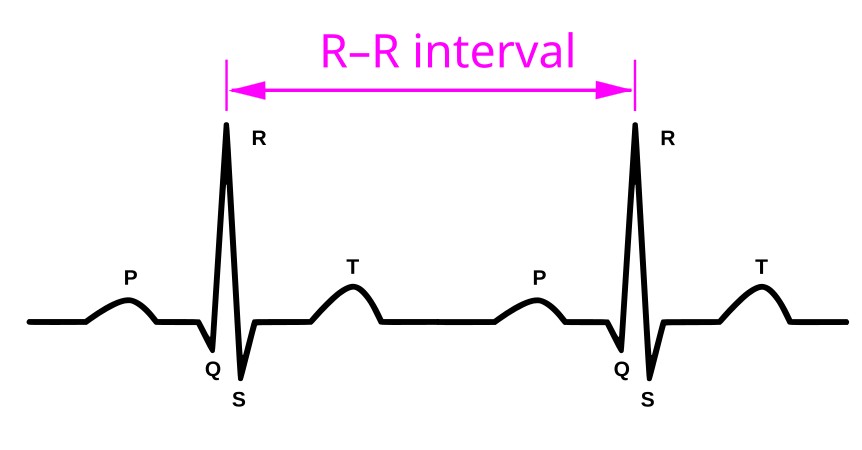
R-R Interval in an ECG
Generally, the heart and brain form a harmonious "marriage"; both need each other and collaborate in life's challenges. However, there are physiological, pathological, or surgical situations in which this good communication breaks down, and the accelerator or brake pedals cease to function properly. At this point, the heart takes control of the biological machinery, disobeying central commands. At this threshold of independence, we find the most surprising mysteries of our organism and its extraordinary constitutional complexity.
The Independence of the Heart
To understand this temporary or permanent disconnection, it is helpful to remember that the first organ to form in the human fetus is the heart. It begins to beat, seemingly without order, to provide oxygen and nutrients to the millions of specialized cells that will form the different organs and tissues, including the brain. We know that it begins beating around the sixth week of gestation, when its development is complete, a crucial moment that allows it to pump blood throughout the body.
From day one, fulfilling its vital function, the heart strives to be part of the ordered microcosm of human biology, while also possessing the powerful capacity to become independent at any moment in the face of certain extraordinary situations, whether internal or external. In fact, modern neurocardiology has highlighted a fundamental finding: "a heart that is too obedient is a vulnerable heart."
When the dialogue breaks down: The arrival of brain signals that are incomprehensible to the heart, which could damage it or create a dangerous scenario for the body due to an excessive response from the autonomic sympathetic nervous system, triggers its aforementioned disobedience and disconnection. An excessive surge of cortisol, adrenaline, and noradrenaline causes a very rapid tachycardia that could lead to ventricular fibrillation or cardiac arrest, forcing the heart to slow down these exaggerated impulses from the nervous system.
On the other hand, the brain can miscalculate, sending disproportionate bursts of vagal tone, known as vasovagal syncope or neurocardiogenic syndrome, in response to certain triggers such as acute pain, significant emotional stress, or prolonged standing. The sudden release of an illogical amount of acetylcholine induces extreme bradycardia or temporary asystole, combined with severe peripheral vasodilation, causing cerebral blood flow to stop and the person to lose consciousness and fall to the ground (fainting, also known as a syncope). At that moment, the heart takes over, regulating heart rate and blood pressure to restore consciousness, since the brain has temporarily ceased functioning.
Sometimes, the brain sends the correct signal, but the heart's internal wiring fails, or ectopic foci of the myocardium decide to act independently. When the specific cardiac electrical conduction system fails to respond, impulses from the sinoatrial node reach the atrioventricular node, but cannot pass through the bundle of His to the ventricles (partial or complete atrioventricular block). This forces the Purkinje network or the ventricular myocardium itself to take control, activating an escape rhythm. The heart then beats at a very slow intrinsic rate (20–40 beats per minute, bpm), completely dissociated from atrial activity and brain control. In situations of cardiac ischemia or significant myocardial damage, multiple ectopic foci generate impulses at extremely high and disorganized heart rates, potentially causing death from ventricular fibrillation or cardiac arrest.
A Definitive Separation
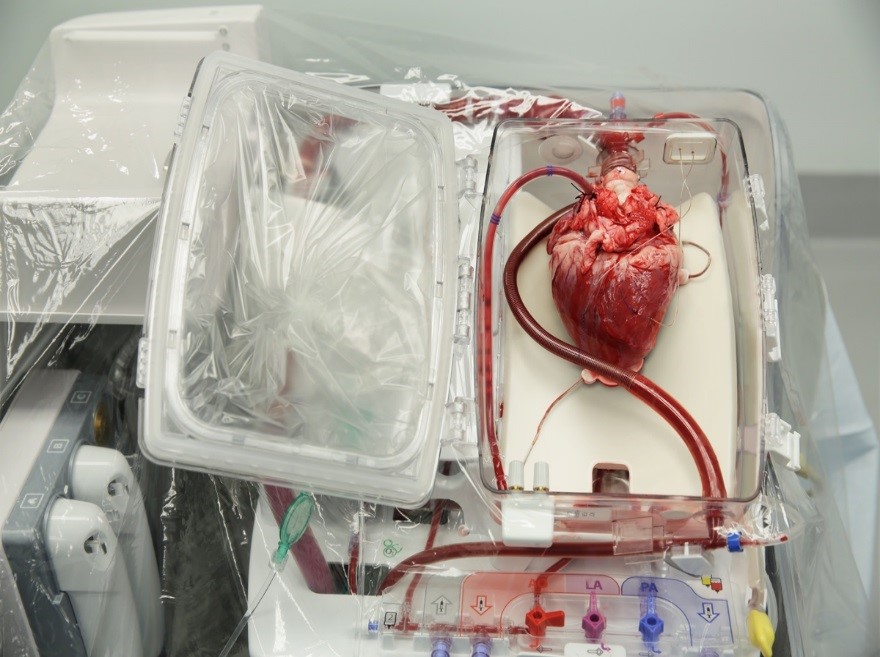
Heart transplant transport system
The most fascinating scenario of forced physiological insubordination occurs after a heart transplant. During the surgical procedure, the parasympathetic (vagal) and postganglionic sympathetic nerve fibers connecting the brain to the donor's heart are irreversibly severed.
In the transplant recipient, lacking the "brake" of acetylcholine, the donor's sinoatrial node operates with an uninhibited intrinsic rhythm, registering a higher resting heart rate (between 90 and 100 bpm). Without the physiological "beat-to-beat adjustment" coordinated by the vagus nerve and the brain, the electrocardiographic tracing of a transplanted heart shows extremely rigid and constant R-R intervals.
During physical exercise, the transplant recipient's brain sends the signal to increase cardiac output, but since there are no direct nerve fibers to the heart, the acceleration is not instantaneous. The heart rate will increase, but gradually, and will take longer to decrease during the recovery phase, as it depends exclusively on the arrival of circulating catecholamines (adrenaline and noradrenaline) secreted by the adrenal glands of the transplant recipient. Furthermore, because the sensory afferent pathways that transmit chest pain to the brain of the transplant recipient are also severed, any episodes of insufficient blood flow to the transplanted heart do not cause the classic angina pectoris, requiring very close and frequent clinical monitoring through echocardiography and specialized tests. It should be noted that "a myocardial infarction in a transplant recipient never causes pain."
The heart's automaticity and its frequent disobedience to the brain's intelligent commands demonstrate that the heart is not a submissive vassal, but a strategic partner endowed with self-governance. Evolution has endowed this marvelous organ with the capacity to sustain itself, through a fascinating biological pacemaker and its own system of neurons. The brain provides the necessary flexibility to adapt to the changing environment, but when the physical or functional connection is interrupted, whether by self-defense, pathology, or the prodigious surgery of transplantation, the heart demonstrates its biological tenacity and justified freedom in defense of life.
“The heart is an organ endowed with such tenacious automatism that it continues beating long after the mind has fallen silent.”
Claude Bernard (1813-1878), French physician, founder of Experimental Medicine.
Personal note: Dr. Revuelta presents in this article something that had been mentioned in “The little brain of the heart”, a prior article he authored, and it resonates with Dr. Randall K. Wolf’s theory that the heart independency (or freedom) exists because of the presence of a larger superficial and smaller deep interconnected network of neurons which are independent of the “classic” nervous system. These are the ganglionated plexi of the heart.
For more information, here are links to videos and articles on this topic:
Article: The Rhythm Control System of the Heart
Article: Conduction System of the Heart
Article: The Heart's Invisible Engineering that Keeps us Alive
Video: Atrial Fibrillation: A Deep Dive into the Autonomic Control of Heart Rhythm
Notes:
1. R-R interval image attribution: ECG-P+QRSkomplex+T.svg: *ECG-PQRST+popis.svg: *SinusRhythmLabels.svg: Created by Agateller (Anthony Atkielski), converted to svg by atom. derivative work: Kychot (talk) derivative work: Kychot (talk) derivative work: Kychot, Copyrighted free use, via Wikimedia Commons. Public domain
2. Heart transplant image attribution: Korozia45, CC BY-SA 4.0, via Wikimedia Commons. Public Domain.
- Details
- Written by: Efrain A. Miranda, Ph.D.
This article is part of the series "A Moment in History" where we honor those who have contributed to the growth of medical knowledge in the areas of anatomy, medicine, surgery, and medical research.



UPDATED: As part of the redesign of this website we added a sidebar called "A Moment in History". The objective is to create a series of articles to honor those individuals who have contributed to the growth of medical knowledge in the areas of anatomy, medicine, surgery, and medical research. Later in the development of the series we became aware of other individuals who have contributed in different ways, but still added their life work to the advancement of medical knowledge, as is the case of Marcia Croker Noyes (1869-1946).
Who would not be moved by the work of Allesandra Gilliani (1307-1326), who is probably the first woman dissector in the history of Human Anatomy, with a tragic short life and a love story.
We also decided to add to this series Moments in History that have left a mark on health care, such as "The First Use of Anesthesia in Surgery", or the story of how many individuals and unknown, anonymous children helped to rid the Americas from the scourge of smallpox, in "The Balmis Expedition",
Another line of articles in this series are those that honor individuals who have used anatomical and surgical knowledge to further other areas of human knowledge, such as that of Juan Vucetich, who used the anatomical differences in fingerprints to create the science of dactiloscopy.
Yet another line of articles are those that are more personal and dear to the contributors of "Medical Terminology Daily", such as "The Ephraim McDowell House of Museum", or "Interesting Discovery in and Ex-Libris".
Recently, I had to work in the Wangensteen Historical Library researching rare and antique medical books. The highlight of this work was to be able to read books by authors whose names are attached as eponyms to anatomical landmarks (Ligament of Treitz, Hesselbach's Triangle), pathologies (Koplik's spots), surgical procedures (Billroth I and II), medical maneuvers (Heimlich maneuver), and surgical instruments (Finochietto retractor). Of course, the names given here are but a small sample of what has been written to date.
As of today this series is now searchable, all you have to do is type "A Moment in History" in our search page, click on the "A Moment in History" link at the top of the sidebar, or click here
The image in this article is that of Dr. Vaclav Treitz. His eponymically named Ligament of Treitz is the most read article in this blog.
Original image, public domain, courtesy of Wikipedia.org.

- Details
- Hits: 938
This article is part of the series "A Moment in History" where we honor those who have contributed to the growth of medical knowledge in the areas of anatomy, medicine, surgery, and medical research.

Hakaru Hashimoto (1881-1934)
Hakaru Hashimoto, was a Japanese surgeon known world-wide today by the thyroid disease that bears his name… Hashimoto’s disease, a condition which causes goiter and hypothyroidism
Hashimoto was born in the village of Iga, about 30 miles (50km) east of Nara, the first permanent capital of Japan on May 5th, 1881. His family had practiced medicine for generations. He was the son and grandson of physicians.
After graduating from high school in Kyoto in 1903, he decided to study medicine at the Fukuoka Medical College of the Kyushu Imperial University and graduated by 1907. He was invited by his professor of surgery at Fukuoka, Hayari Miyake (1867–1945) to stay. Dr. Hashimoto completed his surgical training in 1912. Interestingly, Dr. Hashimoto did his surgical training while Dr. Sunao Tawara (1873 - 1952), discoverer of the heart's atrioventricular node, was a professor of pathology at the same university. For sure their paths crossed more than once!
During his surgical training Dr. Miyake asked Hashimoto to examine the pathological features of four unusual goiter cases, all women over 40 which had been subject to a partial thyroidectomy. At the time it was thought by some that the disease was an initial stage of Riedel’s(*) thyroiditis, which has far more fibrosis than what we know today as Hashimoto’s disease. Riedel’s thyroiditis also presents with rock-hard thyroid glands which adhere to the surrounding tissues making surgery difficult, which was not the case of these four women.
Dr. Hashimoto noted that the histology of these women was similar to Graves’(**) disease (a type of hyperthyroidism) but that both conditions were clinically different, as some of the four patients were hypothyroid.
An important difference was what he found regarding the common colloid goiters. There was a massive overgrowth of lymphatic elements which, as already stated, were similar to Graves goiters.

Illustration from Hashimoto's 1912 publication
Under the guidance of Professor Miyake he reported his findings and named this condition as “Struma Lymphomatosa” publishing an article in German “Zur Kenntniss der lymphomatosen veränderung der Schilddrüse (Struma lymphomatosa)” [On the lymphomatous change of the thyroid gland (struma lymphomatosa).] in the “Archiv für Klinische Chirurgie” in 1912.
He left Japan for Göttingen University in Germany to study with Professor Kaufman, chairman of the Department of Pathology, and worked on tuberculosis of the urinary tract. He left for London in 1914 after the outbreak of World War I where he studied for another year before returning to Japan.
In 1916 he set up a surgical clinic at his own home and married in 1920. Unfortunately, he contracted typhoid fever while working hard against an outbreak in his district in 1933. Dr. Hashimoto died on January 9. 1934. He was 52 years old.
His discovery opened avenues of research leading to great advances in endocrinology and immunology among others. Hashimoto’s disease was finally recognized as an entity by the end of the 1930’s and the term has been widely used since then.
Personal note: This article was suggested and written by my good friend and classmate Dr. Roberto Villaseca Najarian, an endocrinologist in Santiago, Chile. Dr. Miranda.
Sources:
1. Krustrimoviv, N; Fazzino, GFM; Gallo, D. et al. Dr Hashimoto and the discovery of autoimmune hypothyroidism. (PDF) Medicina Historica 2023; Vol. 7, N. 2: e2023034 9
2. Sawin, Clark T. M.D. Hakaru Hashimoto (1881–1934) and His Disease. The Endocrinologist 11(2):p 73-76, March 2001
3. Hashimoto, H. Zur Kenntniss der lymphomatosen veränderung der Schilddrüse (Struma lymphomatosa) Archiv für Klinische Chirurgie, 1912 (PDF)
4. Hashimoto, K. Life and Times: Hakaru Hashimoto. ThyroWorld Spring 2006:16. (PDF)
Notes:
(*) Bernhard Moritz Carl Ludwig Riedel (1846-1916) German surgeon.
(**) Robert James Graves (1796 – 1853) Irish surgeon.
Dr. Hashimoto's portrait, public domain, enhanced via AI
- Details
- Written by: Efrain A. Miranda, Ph.D.
In 1543 Andreas Vesalius was staying at the city of Basel, in Switzerland. The reason for his visit was to oversee the preparation and printing of the first edition of his opus magnum, a book titled ”De Humani Corporis Fabrica, Libri Septem” (Seven Books on the Structure of the Human Body). This book , colloquially known as the “Fabrica”, would change the history of anatomy and become the beginning of scientific, fact-based description of the human body.
The other individual in this story was Jakob Karrer Von Getweiler, a notorious bigamous criminal who lived in Basel. Jakob attacked and stabbed his wife when she confronted him because she found that he had a second wife. Although seriously injured, she survived, but Jakob Karrer was sentenced to death by beheading, a current sentence at the time. The sentence was carried on May 12th, 1543.
 Andreas Vesalius
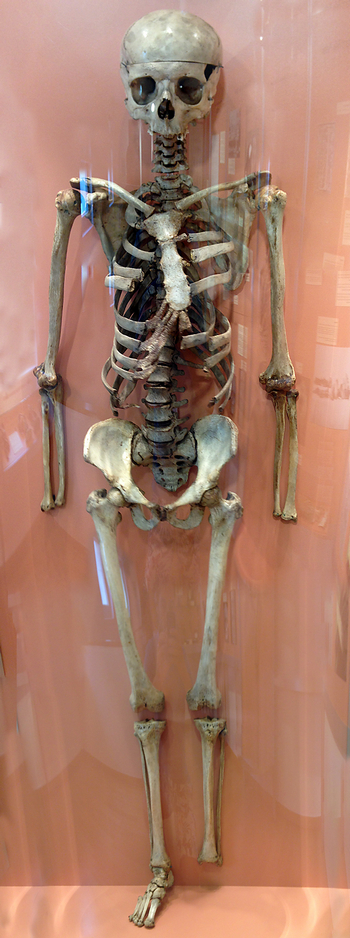
Jakob Karrer Von Getweiler
Because of the laws regarding human dissection (also called anatomizing), only the bodies of executed criminals were permitted to be used as teaching specimens. The dissection was public and anyone, alongside medical students, was permitted to attend. In fact, it was considered public entertainment. Most probably the town council, having a famous anatomist such as Vesalius in town, offered him the opportunity for this public dissection. The title page of the 1555 Fabrica shows this "circus" of a public anatomy with Andreas Vesalius at the center.

1555 Fabrica Title Page
After the dissection, Vesalius proceeded to clean, boil, and dry the bones and, following the instructions in his own book (Book one, Chapter 39), mounted the bones as an anatomical exhibition. Little did Vesalius know that 483 years later, that skeleton would still be in existence and carry the fame of being the oldest anatomical specimen in the world.
Here is the video for the first part of this article.
Additional information found in the Fabrica.

Click for a larger image
Chapter 39 of the Fabrica is extensive and lists in detail how to dissect and clean the bones. One technique is shown in a historiated initial wood block. These were placed at the beginning of chapters. In this case it is the letter “C” of the 1543 Fabrica. The illustration shows three individuals placing the dissected body in a river in a wooden perforated box so that the bones slowly macerated to make it easy to clean all organic matter later.
The next historiated initial is the letter “slanted O” of the 1543 Fabrica. In this image you can see two individuals bringing a head down the gallows while a child holds a basket for the head. This was a preferred technique to study the head without the putrefaction of the rest of the body. The 1555 second edition initial is different, but with the same motif.

1543 edition historiated wood block

1555 edition historiated wood block
The third initial is the “O” in the 1555 Fabrica. This is an important representation using putti. These were images of chubby children, sometimes with wings, common in medieval and renaissance imagery. In this letter we see 5 putti, one of them holding a bone, another tending to the fire under a cauldron and one placing a skull in the boiling water.

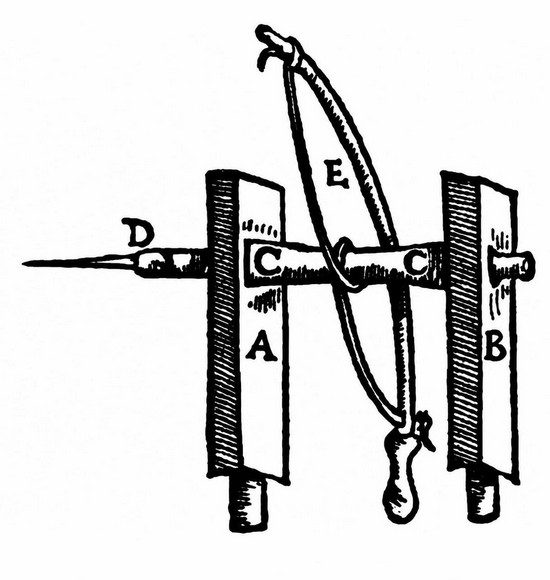
1955 Vesalius bone drill design
In the 1555 second edition of Fabrica, Vesalius added an illustration of a bone drill of his own design, which can be seen here.
In 2023, with the occasion of the Vesalius Triennial Meeting in Antwerp, my friend Dr. Randall K. Wolf and I visited Dr. Francis Van Glabeek, an orthopedic surgeon from Antwerp and an enthusiast of Vesaliana.
We discovered that in 2018 Dr. Van Glabeek had built the bone drill following Vesalius instructions! With my friend Dr. Randall K. Wolf, we were able to operate this drill, that to my understanding is the only one in the world.

Dr. Francis Van Glabeek demonstrating Vesalius' bone drill
Here is the video for the second part of this article.
Sources:
1. "A Bio-blibliography of Andreas Vesalius" Cushing, H. 1943 Saunders
2. Francis Van Glaabek “Une reconstruction du trepan a arc d’André Vésale” 2020 Carnet d’histoire de la Medicine
3. Daniel H. Garrison, Ph.D.; Malcolm Hast MD. "Andrea Vesalius: The Fabric of the Human Body, An Annotated Translation of the 1543 and 1555 Editions of “De Humani Corporis Fabrica Libri Septem". Volume 1/2"; ISBN: 9783318022469 Basel: Karger, A.G., 2014.
4. Lambert, Samuels "Three Vesalian Essays to Accompany the Iconaes Anatomicae of 1934"; New York: MacMillan, 1952.
Note: Image of the skeleton of Jakob Karrer Von Getweiler. Public domain. Amada44, CC BY-SA 3.0 <https://creativecommons.org/licenses/by-sa/3.0>, via Wikimedia Commons
- Details
- Written by: Efrain A. Miranda, Ph.D.
Dr. José Manuel Revuelta
Personal Note: Through my good friend Tito Estrada, I read an very interesting article in Spanish by Dr. Jose Manuel Revuelta. Dr. Revuelta is a Professor of Surgery and Professor Emeritus at the University of Cantabria. Former Head of Cardiovascular Surgery at Valdecilla Hospital in Santander, Spain. Dr. Revuelta contributed the article on "The Little Brain Inside the Heart" which we published in 2025.
The article's title (in Spanish) is "La ingeniería invisible que nos mantiene vivos" (The invisible engineering that keeps us alive), the incredible activity of the cardiac cells and the anatomical description of a helical heart muscle pioneered by Dr. Francisco Torrent-Guasp (1931 - 2005).
He has graciously granted us permission to translate and publish his article in “Medical Terminology Daily”. Dr. Miranda.
The Invisible Engineering That Keeps Us Alive
José Manuel Revuelta Soba
We are talking about a self-exciting, autonomous electrical system, a precision biochemical engine, a power plant capable of changing its "fuel" on the fly to power a very peculiar muscular architecture.
Millennium after millennium, humankind has gazed in awe at this constant pulse that marks the rhythm of life. When we try to repeatedly clench and unclench our fist tightly, in just a few minutes, the fatigue in our forearm forces us to stop. However, just inches away, a muscle the size of that fist contracts rhythmically 100,000 times a day without stopping. For the heart, muscle fatigue is not an option.
How does this organ manage to defy the laws of wear and tear that govern the rest of our biology? There is no man-made engine capable of withstanding such a level of friction and mechanical stress without external maintenance for eight or nine decades. Maintaining that uninterrupted heartbeat is no trivial feat; it's the result of a masterpiece of natural engineering. We're talking about an autonomous, self-exciting electrical system, a precision biochemical engine, a power plant capable of changing its "fuel" on the fly to power a unique muscular architecture.
The Engine That Generates Its Own Electricity
This marvel of endurance begins with an astonishing phenomenon: the heart doesn't wait for orders; it commands itself. Unlike the rest of our muscles, which depend on instructions from the brain, the heart contains a self-sufficient power plant.
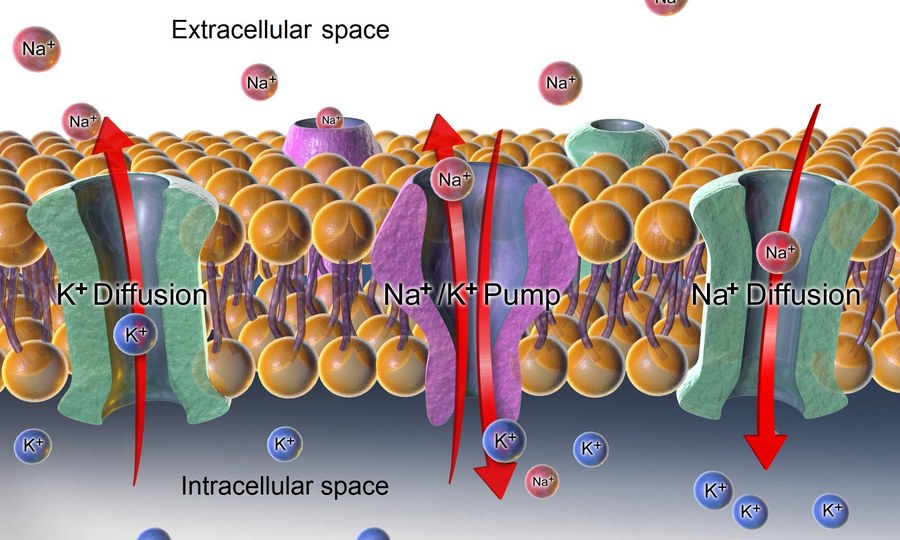
Sodium-Potassium Pump
The secret of this "miracle" lies in a coordinated exchange of minerals. Through microscopic gates located on the surface of the heart cells (ion channels), sodium and potassium ions rhythmically enter and exit. This flow, known as the sodium-potassium pump, creates an electrical potential difference. The result is tiny millivolt discharges that travel through the organ like a controlled shock wave. Each of these impulses—normally between 70 and 80 per minute—propagates through a network of specialized cardiac cells that function like the wiring in a building. This current is what the electrodes of an electrocardiogram (ECG) capture, mapping the activity of our internal "electrical network" on paper.
What is truly remarkable about the heart's electrical system is its redundancy. The main generator (sinoatrial node) sets the pace, but if it fails, the system doesn't shut down; immediately, another backup generator (atrioventricular node) kicks in, capable of activating in milliseconds to maintain the heartbeat. This energy is transmitted through an intracardiac conduction network until it reaches the Purkinje network, the final stretch of wires that makes the muscle contract and keeps life going.
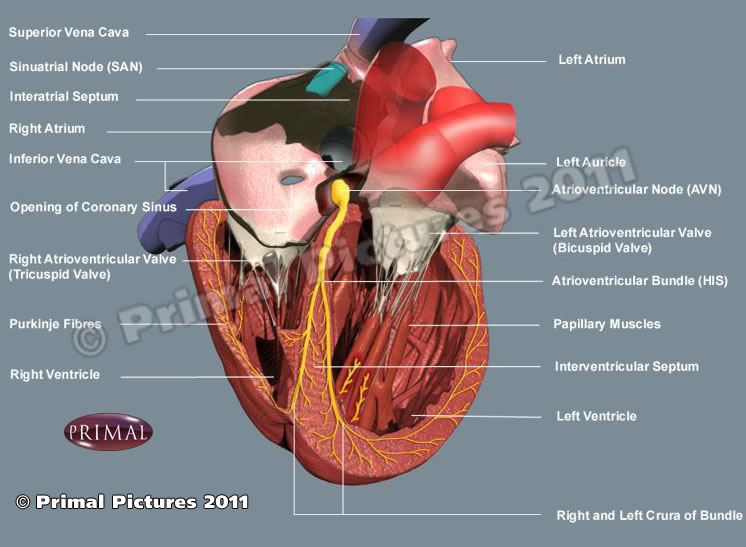
Conduction system of the heart
Amazing Biochemical Engine
If the electrical system generates the spark for ignition, calcium is the inductor that generates the movement. For the heart to contract with the force necessary to pump blood throughout the body, its cells must be flooded with this mineral at high speed. However, managing this flow is not simple: it requires precise biological engineering.
Within the heart cell, there is a specialized reservoir called the sarcoplasmic reticulum. Its function is to store, release, and recover calcium in fractions of a second. It is a closed-loop recycling system that ensures nothing is wasted and that the engine is always ready for the next cycle. When the electrical impulse arrives, ultrasensitive gates burst open, and calcium is released, activating the proteins that trigger contraction (systole). But for the heart to relax and refill with blood (diastole), that calcium must disappear immediately. This is when SERCA (sarcoplasmic/endoplasmic reticulum Ca2+-ATPase) proteins come into play. These proteins act as powerful suction pumps and, in a matter of milliseconds, draw calcium back into the sarcoplasmic reticulum, leaving the muscle relaxed and ready for the next movement.
This cycle of calcium delivery and retrieval occurs about 70 times per minute, but during intense exertion, the system can accelerate to more than 180 cycles per minute without losing synchronization. This ability to manage calcium so quickly and efficiently is what prevents the heart from cramping or becoming fatigued, as happens to our leg muscles after a strenuous run. While other engines might overheat or seize up, the heart uses this perfect recycling cycle to keep running.
A High-Performance Power Plant
If calcium is the messenger of contraction, mitochondria are the boiler that keeps the entire system running. In a typical muscle, mitochondria occupy barely 5% of the cell volume, while in the heart they constitute 35%. They are strategically located on the surface of the cardiac muscle fibers (cardiomyocytes) so that energy transport is practically instantaneous. Unlike other organs that store energy for later, “the heart lives for the day”; it produces and consumes its fuel, a molecule called ATP (adenosine triphosphate), in intervals of 8 to 10 seconds. To move this fuel from the mitochondria, the heart uses phosphocreatine, an ultrafast transport vehicle that guarantees a continuous and uninterrupted flow of energy.
While muscles can work briefly without oxygen—generating lactic acid, responsible for muscle soreness—the heart is an “oxygen addict.” Its metabolism is purely aerobic, allowing it to extract energy from every molecule. The most surprising aspect of this engineering is its flexibility; while the brain only accepts oxygen and glucose, the heart is an “efficient omnivore.” Its preferred fuel is fatty acids, but if the situation demands it, it can burn glucose or even lactate. This ability to switch fuels, depending on availability, ensures that the cell powerhouse (mitochondria) never runs out of supply, whether due to prolonged fasting or intense stress. In short, a perfect balance between energy production and expenditure without any rest.
The Helical Muscular Architecture
For decades, it was believed that the heart was a simple muscular sac that inflated and deflated autonomously. However, thanks to the pioneering vision of the Valencian (from Valencia, Spain) cardiologist Francisco Torrent-Guasp (1931 -2005), we now know that cardiac anatomy is much more sophisticated: the heart is a unique muscular band that coils upon itself in a spiral shape.
To understand how it works, let's forget the idea of a balloon being compressed. Instead, think of a wet towel we want to wring out: we don't press it from the sides, but rather twist it. The heart's engineering follows precisely this principle; its fibers are arranged in a spiral. During systole, the heart rotates on its own axis, performing a "corkscrew" motion. This rotation allows it to expel blood with a force and hemodynamic efficiency that a simple radial contraction could never achieve. But the most ingenious thing happens right at the end of the heartbeat: the elastic unwinding of this muscular band generates a vacuum effect that draws the blood back in. Instead of expending extra energy to fill up, the heart uses its own elastic architecture, it's energy efficiency in its purest form.
In this video, Dr, Torrent-Guasp demonstrates the helical architecture of the musculature of the human heart
Torrent-Guasp spent decades analyzing the hearts of various species in his small home laboratory in Denia, ignored by the scientific community. His luck changed when the prestigious surgeon Gerald Buckberg, from the University of California, Los Angeles (UCLA), recognized the brilliance of his discovery. Buckberg not only disseminated this theory internationally, but also designed a ventricular remodeling surgical technique, which he named "Pacopexy" in honor of his friend Paco Torrent. (Paco is the Spanish nickname for Francisco)
Currently, Torrent-Guasp's concept of the myocardial muscular band is studied at the world's leading universities. It is definitive proof that the heart is not just a muscle, but a marvel of human biology; a continuous muscular structure, without attachment points or independent elements that can fail, designed to adapt to changing hemodynamic pressures throughout a lifetime.
The true genius of the heart's invisible engineering lies not only in its electrical power or its elegant helical geometry, but in a capacity that any engineer would envy: constant self-repair while fully functioning. At the molecular level, proteins damaged by the uninterrupted effort are replaced by new copies without the rhythm being altered in the slightest. It is a unique resilience; we could say that "the heart never rests because it never stops renewing itself."
Ultimately, this organ is a testament to a brilliant biological technology that has perfected the art of enduring, a machine that refuses to surrender to fatigue. Each heartbeat is not just a movement; it is the triumph of the heart's biological engineering.
"What lies behind us and what lies before us are small things
compared with what lives within us"
Ralph Waldo Emerson (1803-1882)
American philosopher and poet.
Notes: The Sodium-potassium pump image public domain, courtesy of Blausen.com staff (2014). "Medical gallery of Blausen Medical 2014". WikiJournal of Medicine (2). DOI:10.15347/wjm/2014.010 ISSN. 2002-4436. Derivative by Mikael Häggström
Resources:
1. Bers, D. Cardiac excitation–contraction coupling. Nature 415, 198–205 (2002).
2. Mora, Vicente, Roldán, Ildefonso, Saurí, Assumpció, Fernández-Galera, Rubén, Monteagudo, Marta, Romero, Elena, Cabadés, Claudia, Cosín, Juan A., Trainini, Jorge C., & Lowenstein, Jorge A. Correspondencia de la deformación miocárdica con la teoría de Torrent-Guasp. Aporte de nuevos parámetros ecocardiográficos. Revista argentina de cardiología, 84(6), 1-2.
3. Website of Dr. Torrent-Guasp and family
4. Buckberg, G., Hoffman, J., Mahajan, A., Saleh S., Coghlan, C. Cardiac Mechanics Revisited: The Relationship of Cardiac Architecture to Ventricular Function. Circulation 118, 24
5. Buckberg G, Mahajan A, Saleh S. Structure and function relationships of the helical ventricular myocardial band. J Thorac Cardiovasc Surg, 2008; 136, 578-589.e11
6. The following 37 minute video was published in 2005 features Dr. Torrent-Guasp and is available on YouTube:
- Details
- Written by: Efrain A. Miranda, Ph.D.

One of my interests is the origin and evolution (etymology) of medical terminology. Because of this, in October 2012 we started on the Clinical Anatomy Associates website a blog called "Medical Terminology Daily". Originally, I thought we could do one article per day… oh how wrong I was!!, but we kept the name and, since then, over one thousand articles have been published.
The first article in the blog was the medical term “Bariatric”. Today we will analyze this term again and the medical derivations that arise from one of these root terms.
The term "bariatric" is a compound word with two Greek roots: βάρος, meaning "weight" or "pressure", and γιατρός meaning "doctor, physician, or healer". The adjectival suffix [-ic] that closes the word means "pertaining to". The term bariatric then means "pertaining to weight-related medicine".
Let’s look at some of the many uses of the root “iatr-“in medical terminology. Remember, you only add an “o” as in “iatr-o” (the combining form of a word) when you are combining a root term with another root or a suffix.
TERM
ETYMOLOGY
(in addition to iatr-)
DEFINITION
Iatrogenic
synonym (nosocomial)
Greek: γέννα (génna) meaning birth, create, produce
Denoting an illness or adverse condition caused by medical treatment or physician intervention
Pediatrics
Greek: παιδί (paidí) meaning child
The branch of medicine dealing with the health and medical care of infants, children, and adolescents
Psychiatry
Greek: ψυχή (psychí) meaning mind/soul
The branch of medicine focused on the diagnosis, treatment, and prevention of mental, emotional, and behavioral disorders
Geriatrics
Greek: γέρος(géros) meaning old.
The branch of medicine dealing with the health and care of old people
Podiatry
Greek: πόδι (pódi) meaning foot
The branch of health care dedicated to the study, diagnosis, and treatment of disorders of the foot
There are variations of the suffixes added to the root term iatr-. Examples of these are:
-iatry - denoting the field of practice, such as pediatry, podiatry, psychiatry. etc.
-iatrist - the person practicing that particular field, such as psychiatrist, geriatrist, etc.
-iatrician - another way of denoting the field of practice, such as pediatrician.